Cms L564 Printable Form
Cms L564 Printable Form - The person applying for medicare completes all of section a. Write the name of your employer. Social security administration telephone number: Write the date that you’re filling out the request for employment information form. Write the date that you’re filling out the request for employment. You retired within the last 8 months. To be completed by individual signing up for medicare part b (medical insurance) 1. Write the name of your employer. Web form cms l564/r297 (08/20) 2 fform approved omb no. The person applying for medicare completes all of section a.

Commercial Loan Application Form Financial Report

1990 Form CMS40B Fill Online, Printable, Fillable, Blank pdfFiller
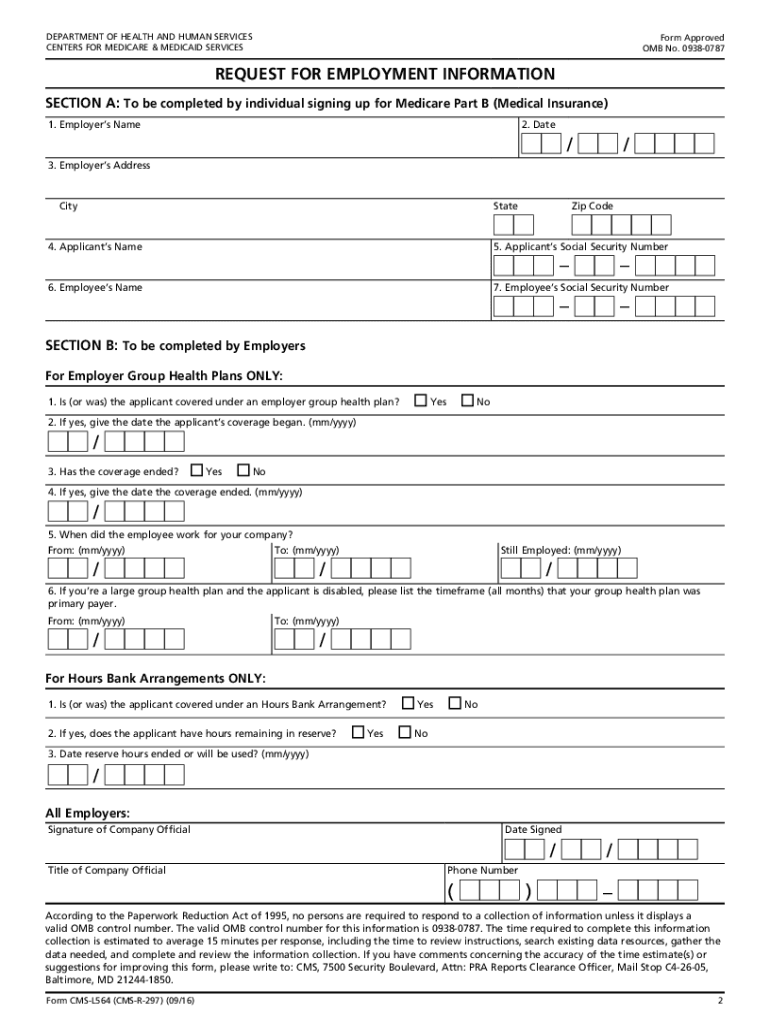
CMSL564 2016 Fill and Sign Printable Template Online US Legal Forms

Form CmsL564 Request For Employment Information, Medicare True/false
Medicare Part A Application Form Medicare Id Card Sample Inspirational

Medicare Part B Application Form Cms L564 Form Resume Examples

Medicare Part B Application Form Cms L564 Universal Network

2010 Form CMSL564 Fill Online, Printable, Fillable, Blank pdfFiller

Gallery of Medicare Part B Enrollment form Cms L564 New 54 Awesome

Cms L564 Printable Form Master of Documents
You Retired Within The Last 8 Months.
Web form cms l564/r297 (08/20) 2 fform approved omb no. Write the date that you’re filling out the request for employment information form. To be completed by individual signing up for medicare part b (medical insurance) 1. Giving the social security administration proof you’re eligible to sign up for part b if:
The Person Applying For Medicare Completes All Of Section A.
Write the name of your employer. Social security administration telephone number: Write the name of your employer. Department of health and human services centers for medicare & medicaid services form approved omb no.
The Person Applying For Medicare Completes All Of Section A.
Write the date that you’re filling out the request for employment. If you delayed enrolling in medicare because you had coverage through your job, use this form to enroll during your special enrollment period (sep).