Free Printable Release Of Information Form
Free Printable Release Of Information Form - Download a medical records release (hipaa) form to authorize healthcare providers to release medical information. Download our hipaa release form using the link on this page. A medical records release authorization form is a document that allows a person to disclose protected health information to a third party. Meet your privacy obligations under hipaa with this authorization to release medical information form. **authorization for use or disclosure of protected health information (required by the health insurance portability and accountability act, 45 c.f.r. Free immediate download of medical relasese form pdf. Explain to your patient that they are authorizing you to disclose their protected health information. You can also get a copy from the carepatron app or our resources library. (name of patient) this information is to be released for the purpose stated above and may not be used by recipient for any other purpose. Please complete all sections of this hipaa release form.

Release Of Information Forms Printable (BLANK TEMPLATE)

FREE 9+ Sample Release of Information Forms in MS Word PDF

FREE 13+ Sample Release of Information Forms in PDF MS Word
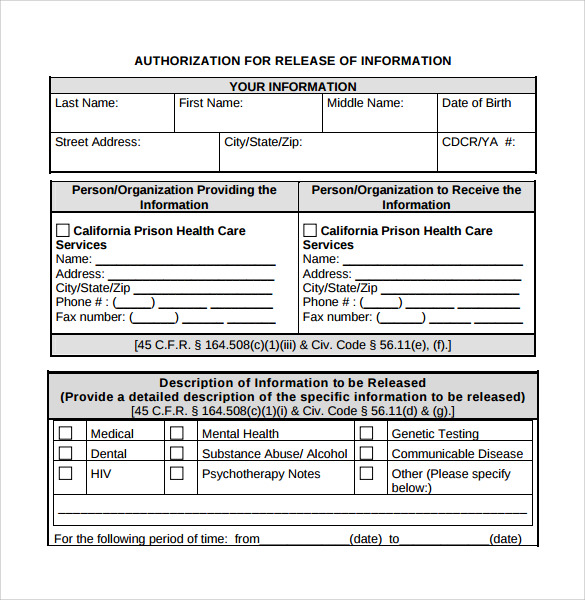
FREE 8+ Sample Release Of Information Forms in PDF MS Word

Free General Release Of Information Form Template PRINTABLE TEMPLATES

Release Of Information Forms Printable (BLANK TEMPLATE)

FREE 8+ Sample Release Of Information Forms in PDF MS Word

Release Of Information Form Download Printable PDF Templateroller

FREE 10+ Sample Release of Information Forms in PDF Word Excel

FREE 8+ Sample Release Of Information Forms in PDF MS Word
Free Immediate Download Of Medical Relasese Form Pdf.
Always stay on top of your patient's health concerns, and safeguard their details with ease. Direct free access to pdf of hipaa release. A patient can also request their medical records not currently in their possession. **authorization for use or disclosure of protected health information (required by the health insurance portability and accountability act, 45 c.f.r.
(Name Of Patient) This Information Is To Be Released For The Purpose Stated Above And May Not Be Used By Recipient For Any Other Purpose.
You can also get a copy from the carepatron app or our resources library. Meet your privacy obligations under hipaa with this authorization to release medical information form. Explain to your patient that they are authorizing you to disclose their protected health information. This form is for use when such authorization is required and complies with the health insurance portability and accountability act of 1996 (hipaa) privacy standards.
A Medical Records Release Authorization Form Is A Document That Allows A Person To Disclose Protected Health Information To A Third Party.
Download our hipaa release form using the link on this page. I, ____________________________________hereby voluntarily authorize the disclosure of information from my health record. If any sections are left blank, this form will be invalid and it will not be possible for your health information to be shared as requested. Please complete all sections of this hipaa release form.